State Category: New York

U.S. Adult Obesity Rates Hold Steady Amid Recent Upheavals to Nutrition and Prevention Policies and Programs
Special Feature Examines Challenges and Implications of Implementing New Dietary Guidelines in Federal Nutrition Programs
(Washington, DC — September 24, 2026) A new Trust for America’s Health (TFAH) report finds that 21 states had adult obesity rates at or above 35 percent in 2025. The 2025 total falls between the 19 states recorded in 2024 and the 23 states recorded in 2023. By contrast, no state had reached a 35 percent threshold in 2012.
The report, State of Obesity: Better Policies for a Healthier America 2026, is based in part on TFAH’s analysis of newly released 2025 data from the Centers for Disease Control and Prevention’s (CDC) Behavioral Risk Factor Surveillance System (BRFSS) and data from the 2021-2023 National Health and Nutrition Examination Survey (NHANES).
Key findings from the report include:
- The nation’s overall obesity rate continues to be high. Nationally, 4 in 10 American adults have obesity. Obesity rates are increasing among children and adolescents, with just over 21 percent of U.S. children and adolescents, ages 2 to 19, having obesity nationwide. (2021–2023 NHANES)
- Two states, Louisiana and West Virginia, saw statistically significant decreases in their adult obesity rates between 2024 and 2025. Louisiana went from 39.2 percent in 2024 to 35.6 percent in 2025. West Virginia went from 41.4 percent in 2024 to 37.4 percent in 2025. No state had statistically significant increases. (2025 data from BRFSS)
- Differences in the adult obesity rates between states remain considerable, with a low of 25.7 percent in Colorado and 26.4 percent in Hawaii — as well as 24.2 percent in the District of Columbia — to a high of 39.7 percent in Alabama, 39.1 percent in North Dakota, and 38.8 percent in Kentucky. (2025 data from BRFSS)
This year’s report release comes amid significant changes to the nation’s approaches to preventing chronic disease, including the increase in use of GLP-1 medications and a renewed emphasis on promoting healthy eating. At the same time, fewer people have access to nutrition supports, and federal programs intended to prevent chronic disease have seen their capacity significantly weakened.
Despite an increased national focus on healthy eating, provisions in the One Big Beautiful Bill Act have reduced access to healthy, affordable meals at a time of higher food costs. Five million people — including an estimated 1.5 million children — have already lost access to the Supplemental Nutrition Assistance Program (SNAP), a critical source of food and nutrition security for many Americans. The CDC’s National Center for Chronic Disease Prevention and Health Promotion also lost more than 200 staff through reductions in force, and the U.S. Department of Agriculture’s (USDA) restructuring plan may cause significant staff shortages in the offices that support federal nutrition programs like SNAP and the Special Supplemental Nutrition Program for Women, Infants, and Children (WIC).
The President’s fiscal year 2027 budget also calls for eliminating the Division of Nutrition, Physical Activity, and Obesity and reorganizing and cutting funding for many longstanding chronic disease prevention activities previously housed in CDC’s National Center for Chronic Disease Prevention and Health Promotion under the proposed Administration for a Healthy America. If enacted, the President’s budget would eliminate many obesity and chronic disease prevention programs, such as the State Physical Activity and Nutrition Program, the Preventive Health and Health Services Block Grant Program, and the National Diabetes Prevention Program.
“After decades of rising obesity rates in this country, we are finally starting to see adult rates stabilize. These data are encouraging, but we cannot afford to lose momentum. Our goal remains ensuring every person has the opportunity to be as healthy as possible,” said J. Nadine Gracia, M.D., MSCE, President and CEO of TFAH. “Eliminating proven obesity prevention programs and reducing food security for millions of people put the health and economic well-being of Americans at risk.”
A special feature in this year’s report examines the new Dietary Guidelines for Americans and their implications for food and nutrition programs like school meals, WIC, and the Child and Adult Care Food Program (CACFP). The Dietary Guidelines aim to serve as a model for individuals to follow as they make dietary decisions for themselves and their families. They also are a foundation for the standards for federal food and nutrition programs that reach millions of Americans every year.
When new Dietary Guidelines are released, USDA typically develops guidance for federal food and nutrition programs to align them with the new Dietary Guidelines. This includes federal nutrition programs like the National School Lunch Program, which feeds 30 million children every day; WIC, which serves 6.9 million parents and children every year; and CACFP, which serves 4.8 million children annually.
To date, USDA and the U.S. Department of Health and Human Services have not issued new overarching nutrition standards or guidance to align school meals, CACFP, WIC, or other nutrition programs with the 2025–2030 Dietary Guidelines. Both agencies have indicated that they will soon issue guidance and have rolled out various voluntary pledges for schools, hospitals, and other settings to make updates to the food they serve.
The report authors highlight some of the challenges of implementing the new Dietary Guidelines in federal nutrition programs: reducing processed foods requires more staff time, kitchen equipment, and often major infrastructure investments; and added sugars are pervasive across many staple foods, including bread and yogurt. These will be crucial considerations when USDA issues new guidance on nutrition standards for school meals and other nutrition programs.
“CACFP operators are caregivers first and foremost. They support children and older adults every day while providing nutritious meals alongside many other responsibilities,” said Alexia Thex, M.Ed., President of the National CACFP Association. “Successfully implementing new nutrition standards will require investment, training, and ongoing support.”
In the feature section, TFAH recommends strengthening future Dietary Guidelines by ensuring they adhere to rigorous scientific and process standards, improving access to healthy foods and resources for nutrition programs and the public, and strengthening the guidelines’ educational components.
Policymakers can address root causes of obesity by making healthy food and physical activity accessible, affordable, and convenient. The report includes recommendations for policy action by the administration, Congress, and states to address the nation’s obesity crisis, including:
- Congress should support public health infrastructure by increasing investments in CDC’s National Center for Chronic Disease Prevention and Health Promotion and the Division of Nutrition, Physical Activity and Obesity to support prevention activities across the country.
- The administration should ensure federal public health agencies are fully staffed to carry out their missions.
- Congress should work to improve nutritional quality and nutrition security by reversing the changes to the SNAP program in the One Big Beautiful Bill Act that have led to reduced SNAP access for families in need.
- Federal and state policymakers should expand access to healthy school meals for all schoolchildren.
- Policymakers should institute sugary beverage taxes to discourage consumption of unhealthy foods, while funding public health initiatives.
- The U.S. Food and Drug Administration should create and implement a mandatory front-of-package nutrition label system for packaged foods to help consumers make informed choices.
- Congress should close tax loopholes and eliminate business-cost deductions related to the advertising of unhealthy food and beverages to children.
- Policymakers should support programs like Academic Enrichment Grants and Every Kid Outdoors that encourage physical activity in childhood, setting children up with a foundation for a healthy, active lifestyle.
- Localities should implement Complete Streets and Vision Zero transportation plans that prioritize safe, active transportation.
Read the full report
###
Trust for America’s Health is a nonprofit, nonpartisan public health policy, research, and advocacy organization that promotes optimal health for every person and community and makes the prevention of illness and injury a national priority.
New report: Chronic Underinvestment and Recent Disruptions Have Weakened U.S. Public Health System
TFAH calls for sustained investment and stronger capacity
(Washington, D.C. – September 10, 2026) – A new report released today by Trust for America’s Health (TFAH), a nonpartisan, nonprofit organization focused on public health research and policy, finds that America’s public health system is at an inflection point. Decades of chronic underinvestment, compounded by workforce reductions, funding disruptions, and institutional uncertainty during 2025 and 2026, have weakened the system’s capacity to protect communities from preventable disease and injury.
The report, Underfunded and Under Strain: The State of America’s Public Health System, calls for restoring federal public health operating capacity and establishing more durable and predictable funding to ensure that public health agencies have the staffing, expertise, infrastructure, and continuity needed to carry out their missions effectively.
The public health system is a network of agencies, organizations, public health workers, and community programs working together to prevent illness and injury, promote health, and respond to health threats—helping people and communities live healthier, safer lives.
The report finds that the system entered 2025 with longstanding funding, workforce, and infrastructure vulnerabilities that left it with little margin to absorb additional disruption. In 2024, only about 3 percent of the nation’s $5.3 trillion in health expenditures went to governmental public health activities.
Congress preserved much of the federal public health system in fiscal year (FY) 2026, but appropriations alone could not restore lost operating capacity. The Consolidated Appropriations Act, 2026 maintained the Centers for Disease Control and Prevention’s (CDC) program-level funding at approximately $9.1 billion—essentially flat with FY 2025—and rejected many of the administration’s deepest proposed cuts while preserving core agency structures. But by May 2026, CDC’s workforce had fallen by approximately 3,600 from the end of FY 2024, a reduction of roughly 28 percent. Grant interruptions, funding delays, and diminished technical and administrative capacity also continued to affect program operations.
The result illustrates a central finding of the report: appropriated dollars are critical, but they are not sufficient to ensure that public health programs can function effectively. Staffing, institutional expertise, grant-administration capacity, technical assistance, stable relationships with grantees, and timely disbursement of funds all help determine whether appropriations translate into services and protections for communities.
“We have a public health system that was already under strain, and workforce, funding, and institutional disruptions have intensified that strain,” said Dr. J. Nadine Gracia, President and CEO of TFAH. “We need predictable and reliable funding, along with sufficient staffing and expertise, to restore capacity and establish a more durable public health foundation that supports the health and well-being of all people and prepares the nation for future public health emergencies.”
If enacted, the FY 2027 President’s Budget Request would deepen the erosion of federal public health capacity. The proposal moderates some elements of the administration’s FY 2026 request but retains its central direction: a smaller federal public health footprint and a narrower and reorganized CDC with less funding and personnel to carry out programs and activities. Although the proposal would maintain or increase funding for selected capabilities, including some aspects of infectious disease surveillance, data modernization, immunization, food safety, and global health, it also would:
- Eliminate the Prevention and Public Health Fund, a dedicated funding stream that supports prevention and public health programs nationwide.
- Consolidate HRSA, SAMHSA, and major CDC programs into a new Administration for a Healthy America with significantly less funding to support program activities, risking disruption to specialized expertise and established partnerships.
- Reduce total resources supporting functions historically housed at CDC and the Agency for Toxic Substances and Disease Registry by approximately $2.86 billion, or 31 percent, even after accounting for funding proposed to follow programs transferred to other HHS components.
- Create a new National Center for Chemicals and Toxins within CDC while reducing funding for the programs proposed to comprise the center by approximately $718 million relative to FY 2026.
- Substantially reduce broad-based prevention and public health capacity, including chronic disease and injury prevention, state and local preparedness, foundational infrastructure, domestic HIV prevention, and several environmental and occupational health functions.
The report cautions that the risk is not limited to enactment of the proposed cuts. Even if Congress again rejects the deepest reductions, continued flat funding, workforce attrition and hiring constraints, grant-administration disruptions, and sustained uncertainty could further erode public health capacity. Reversing that trajectory will require rebuilding capacity, not simply preserving funding levels.
At the same time, demands on the public health system remain high. Measles outbreaks, declining childhood vaccination rates, foodborne outbreaks, extreme heat, the epidemics of overdose and suicide and other health threats are testing capabilities that depend on a functioning public health infrastructure—including emergency readiness, environmental and workplace protections, chronic disease and injury prevention, and the capacity of less-resourced communities to prepare for and respond to health threats. These capabilities also support the nation’s economic and national security.
The report features interviews with two public health officials—Dr. Daniel Edney, State Health Officer of Mississippi, and Dr. Michelle Taylor, Commissioner of Health for the Baltimore City Health Department—who describe what federal funding and operational uncertainty have meant on the front lines.
“When CDC is hurting, that hurts public health in Mississippi,” Dr. Edney said. Dr. Taylor described how that uncertainty complicates planning even when funding still appears on paper. “Funding may appear in the budget line, but everybody who leads a local or state health department, along with all their staff, understands that in the current environment, just because it’s on a line in a funding document doesn’t mean it’s going to stay there,” Dr. Taylor said.
To protect the nation’s health, economic security, and national security, the report recommends that Congress and the administration take steps to restore and strengthen the public health system, including:
- Restore federal health agency operating capacity. Rebuild staffing, expertise, grant administration, technical assistance, and other operational capacity needed to carry out funded programs and statutory responsibilities.
- Preserve complementary federal capabilities. Preserve and strengthen the distinct roles of CDC, the Substance Abuse and Mental Health Services Administration, the Health Resources and Services Administration, the Administration for Community Living, the Administration for Strategic Preparedness and Response, and other federal health agencies. Any major restructuring should proceed only through a bipartisan, deliberative process with congressional oversight and stakeholder input.
- Strengthen CDC as a comprehensive national public health agency. Provide at least $11.58 billion for CDC in FY 2027, followed by sustained increases, and preserve its responsibilities across infectious disease, chronic disease, injury prevention, environmental and occupational health, preparedness, and foundational infrastructure.
- Ensure that appropriated funds are spent as intended. Release funds promptly and prevent awards from being delayed or terminated for reasons unrelated to statutory purposes, performance, or compliance.
- Provide durable and predictable financing. Enact full-year appropriations on time, restore and protect the Prevention and Public Health Fund, and reject new discretionary funding caps that hinder public health modernization and readiness for evolving health threats.
- Invest in foundational infrastructure and health security. Sustain workforce, laboratory, epidemiology, data-modernization, and cross-cutting health department capacity, and create a Health Defense Operations budget designation for programs central to the nation’s health, economic, and national security.
Read the full Public Health Funding report
In tandem with the report, TFAH has also launched the Public Health Programs Monitor, a nonpartisan initiative with an interactive dashboard that tracks selected federal health-promoting programs and operational activities across HHS. The monitor brings together budget information and proposed and actual program changes, along with analysis that helps explain how federal funding, staffing, and administrative decisions affect public health programs and the communities they serve.
###
Trust for America’s Health is a nonprofit, nonpartisan public health policy, research, and advocacy organization that promotes optimal health for every person and community and makes the prevention of illness and injury a national priority.
Chronic Underinvestment and Recent Disruptions Have Weakened U.S. Public Health System

Age-Friendly Public Health: The Podcast

August 2026
In this episode of Age-Friendly Public Health: The Podcast, host J. Nadine Gracia, President and CEO of Trust for America’s Health (TFAH), is joined by Rani Snyder, President of The John A. Hartford Foundation. Their conversation explores the future of healthy aging and the Foundation’s vision for advancing age-friendly care, supporting family caregivers, and improving systems that serve older adults. Dr. Gracia and Ms. Snyder also discuss the importance of cross-sector collaboration among public health, healthcare, philanthropy, and community organizations, as well as opportunities to strengthen the role of public health in helping people age well. Looking ahead, they consider the investments, partnerships, and policy changes needed to build age-friendly systems that are prepared to meet the needs of a growing older population.
Transcript: A Vision for Healthy Aging: Grounded in Partnerships
Season Three Episodes:
- Aging Well in Rural America: Partnerships, Policy, and Progress
- The Intersections Between Aging and Disability Policy
Season Two Episodes:
- Partnering with the YMCA to Advance Age-Friendly Work
- The Intersections Between Aging and Disability Policy
- Partnering with the YMCA to Advance Age-Friendly Work
Season One Episodes:
- Ageism – Its Impact and How to Overcome It
- Building Strategic Partnerships to Create Age-Friendly Communities
- Building an Age-Friendly Ecosystem in Mississippi
- Where it all Began
You can listen on Apple Podcasts, Spotify or where ever you access your favorite podcast.
Age-Friendly Public Health: The Podcast is a production of Trust for America’s Health’s (TFAH) Age-Friendly Public Health Systems Initiative. This quarterly podcast, hosted by TFAH’s President and CEO Dr. J. Nadine Gracia, will feature conversations with leaders in the age-friendly public health systems movement on challenges, opportunities, and model programs, with a focus on the role public health can play in helping older adults thrive.
Trust for America’s Health Statement in Response to Executive Order on Childhood Vaccine Recommendations
(Washington, DC – August 11, 2026) – Yesterday’s executive order sets forth an unprecedented change to childhood vaccine recommendations. For decades, the childhood immunization schedule has been the product of extensive scientific research, clinical experience, and independent expert review. The executive order bypasses this trusted and transparent process and creates needless barriers to access.
Vaccines are among the most effective tools available to prevent serious, painful, and sometimes deadly diseases. When children receive recommended immunizations on schedule, they are protected against preventable illness, families and communities have reduced risk of outbreaks, and children have a greater opportunity to grow up healthy and strong. If implemented, the changes put forward under the executive order would undermine confidence in vaccines, make it harder for clinicians to give consistent guidance and ensure consistent uptake, and create additional barriers to families trying to keep their children safe.
Ensuring children receive the protection they need requires rigorous science and careful review – not less. Every child deserves policies grounded in the best available science, guided by trusted experts, and focused on giving children the strongest possible foundation for their future.
Combined Deaths from Alcohol, Drugs and Suicide Declined by 16% in 2024
New Report Highlights How Progress is at Risk Amid Federal Workforce and Funding Cuts; Special Feature on Suicide Sheds Light on Disparities
(Washington, D.C. – June 2, 2026) – The death rate from alcohol-induced, drug overdose, and suicide causes were each down significantly in the United States in 2024 for the first time since 1999 (when datasets were initially published), and provisional data for 2025 signals this positive trend has continued.
A new report from Trust for America’s Health (TFAH) explores what’s behind these recent downward trends, which demographic groups are still experiencing high rates of death from these causes, and how federal workforce and funding cuts are putting progress at risk.
Pain in the Nation 2026: The Epidemics of Alcohol, Drug, and Suicide Deaths, which examines data from the Centers for Disease Control and Prevention (CDC) and other federal sources, finds that the combined age-adjusted rate of deaths from alcohol, drugs, and suicide declined by 16 percent in 2024, building on a decrease of 4 percent in 2023. Specifically, alcohol-induced mortality declined by 4 percent, drug overdose mortality by 26 percent, and suicide mortality by 3 percent.
Most states saw improvements in their combined rates as well: 45 states and the District of Columbia had lower rates compared to 2023, four states had higher rates (Iowa, North Dakota, South Dakota, and Wyoming), and one state stayed the same (Nebraska) in 2024.
Cuts to public health workforce and funding, as well as uncertainty surrounding long-standing federal programs and grants, significantly threaten this progress. For example, the CDC’s National Center for Injury Prevention and Control (Injury Center), Substance Abuse and Mental Health Services Administration (SAMHSA), Veterans Affairs health care staff, and 988 Suicide and Crisis Lifeline’s LGBTQ+ youth services all experienced cuts or eliminations, despite the critical role these programs have in reducing deaths from these causes.
“Sustaining and building on recent progress requires the federal government to invest even more in programs that reduce and prevent harm—not cut them—while also investing in the skilled workforce and modern data systems necessary to deliver and evaluate those programs effectively,” said Dr. J. Nadine Gracia, President and CEO of TFAH. “We are also seeing specific groups of people not experiencing the same progress, especially when it comes to deaths from suicide, meaning we need to do even more to build strong policies and programs that help to improve everyone’s mental health and well-being,”
The report examines the strategies, policies, and programs that have helped drive the recent decline in mortality, including:
- Creating and sustaining new federal programs and infrastructure, including prevention grants such as SAMHSA’s Garrett Lee Smith program (2004) and the CDC’s Comprehensive Suicide Prevention program (2020) and Preventing Adverse Childhood Experiences through Data to Action (2023).
- Investments in data systems, like CDC’s Overdose Data to Action and the National Violent Death Reporting System, have allowed health officials to track emerging trends by geographic, demographic, and drug type metrics to guide local, state, and national responses and to prevent overdoses and deaths in real time in communities in need.
- A growing focus on the drivers of substance misuse and poor mental health through prevention and early intervention policies, including improving social, environmental, and economic conditions; expanding resilience programs in schools; and increasing access to social and mental health services for children and families.
Pain in the Nation includes a special feature on suicide, which was the 10th leading cause of death in 2024 and the second leading cause of death for people ages 10–14, 15–24, and 25–35. Key findings related to suicide include:
- Suicide rates across nearly all racial and ethnic groups were lower in 2024, after peaks in 2022 or 2023. Despite this progress, American Indian and Alaska Native people consistently have the highest suicide rate of any race/ethnicity.
- Historically, Black youth have had relatively low suicide mortality rates compared to their peers, but rates have risen at an alarming pace in recent decades, increasing 144 percent from 2007 to 2020.
- Suicide rates are higher in rural areas compared with urban areas and have increased at a faster rate over the last two decades. The most recent data available, from 2022, show that rural areas had a suicide rate 41 percent higher than urban areas.
- While the rate of suicide deaths is unknown for LGBTQ populations, research consistently find higher rates of mental health issues, substance use, and suicidal behaviors for LGBTQ individuals compared with heterosexual individuals.
The report also calls for a sustained commitment to primary prevention programs and investments, and includes recommendations on actions the Administration, Congress and federal agencies should take, such as:
- Investing in prevention and conditions that promote health
- Spend behavioral health funds and carry out investments as directed by Congress.
- Provide robust funding for CDC’s Injury Center and maintain the vital workforce necessary to fulfill the Center’s activities.
- Support policies and programs that reduce adverse childhood experiences and the impact of trauma and promote positive childhood experiences.
- Reducing overdose risk and access to lethal means of suicide
- Support policies to reduce overdose and bloodborne infection.
- Support efforts to limit access to lethal means of suicide, such as safe storage of medications and firearms.
- Transforming the mental health and substance use prevention system
- Maintain SAMHSA’s funding and critical workforce and bolster the continuum of crisis intervention programs and supports, such as the 988 Suicide and Crisis Lifeline.
- Restore Medicaid funding and eligibility to prevent losses in mental health and substance use healthcare.
- Promote equity in mental health, with a specialized workforce and targeted services to reduce disparities in access and outcome.
Read the full report
Preparedness for Public Health Emergencies at Risk Amid Federal Funding and Workforce Instability, New Report Finds
Ready or Not 2026 finds wide variation in state preparedness and warns that federal disruption could weaken emergency readiness nationwide
(Washington, DC – May 7, 2026) – Amid deep federal staffing cuts, grant terminations, and other far-reaching changes to the federal public health system, a new report from Trust for America’s Health (TFAH) finds wide variation in states’ readiness for disease outbreaks, natural disasters, and other health emergencies. The report warns that national preparedness depends not only on state capacity, but also on strong and stable federal health and preparedness systems, sustained intergovernmental coordination, and long-term investment in public health infrastructure.
Ready or Not 2026: Protecting the Public’s Health from Diseases, Disasters, and Bioterrorism measures the nation’s readiness for public health emergencies through 10 indicators of state preparedness, including healthcare workforce mobility, state public health funding, laboratory surge planning, access to paid sick leave, and community water system safety. This year’s report also includes a special feature on how federal workforce reductions and funding instability could weaken preparedness nationwide.
“The nation faced the most severe flu season in nearly a decade, the highest annual measles case count since 1991, and devastating weather-related emergencies, even as federal public health funding, staffing, and operational support were destabilized,” said Dr. J. Nadine Gracia, President and CEO of TFAH. “These challenges make clear that emergency preparedness cannot rely on a patchwork of limited and unpredictable resources. Effective readiness requires strong federal leadership, stable investment, and coordinated action across states and communities, especially as the United States prepares to host matches during the 2026 World Cup.”
As TFAH marks its 25th anniversary, the report highlights how decades of federal investment, policy development, and programmatic progress helped build the preparedness systems now under strain. The report places states and the District of Columbia into three performance tiers for emergency preparedness: 20 states in the high-performance tier, 17 states and the District of Columbia in the middle-performance tier, and 13 states in the low-performance tier.
High-Performance Tier – 20 states
CA, CO, CT, DE, FL, IL, KS, MA, MD, ME, MT, NC, NH, NJ, PA, RI, UT, VA, VT, WI
Middle-Performance Tier – 17 states and the District of Columbia
AR, AZ, DC, GA, HI, ID, IN, LA, MO, ND, NE, NV, NY, OH, OR, SC, TN, WA
Low-Performance Tier – 13 states
AL, AK, IA, KY, MI, MN, MS, NM, OK, SD, TX, WV, WY
These benchmarks provide policymakers and health officials with a roadmap for strengthening emergency preparedness in their jurisdictions.
Other key findings from the report include:
Public Health Funding: Most states increased or maintained their public health funding in fiscal year 2025. At least 12 states reduced state public health funding.
Water Safety: On average, 6 percent of residents in each state were served by a community water system with at least one health-based violation, mainly concentrated in smaller, rural, and socioeconomically disadvantaged communities. A federal assessment also found critical or high-risk cybersecurity vulnerabilities in dozens of drinking water systems.
Seasonal Flu Vaccination: The percentage of U.S. residents who received a vaccination against influenza continued to decrease from pre-COVID-19 pandemic levels. The 2024-25 flu season saw the highest hospitalization rates since 2010–2011 and the most pediatric deaths in any non-pandemic season since reporting began in 2004.
Avoidable Mortality: Wide variation persists across states in deaths from preventable and treatable causes before age 75. Rates in the highest-burden states are more than twice those in the lowest. Racial and ethnic disparities compound these gaps in most states, and low overall rates do not necessarily indicate equitable outcomes.
Paid Sick Leave: Access to paid sick leave varies widely across U.S. regions—from 98 percent of workers in Pacific states to 67 percent in East South Central states—and gaps are most concentrated among low-wage, part-time, and service-sector workers. Paid sick leave reduces disease transmission, supports business continuity, and is increasingly recognized by employers as an important part of preparedness infrastructure.
Policy Recommendations for Improving Emergency Preparedness:
The report outlines steps the Administration, Congress and federal agencies should take to strengthen the nation’s health and economic security:
- Provide stable, flexible, and sufficient funding for public health preparedness, workforce, and data modernization to help ensure every state has the systems needed to protect residents.
- Restore the federal public health workforce and capabilities reduced in 2025.
- Reauthorize the Pandemic and All-Hazards Preparedness Act.
- Strengthen outbreak and pandemic readiness by supporting immunization, public health surveillance, and antimicrobial resistance efforts.
- All levels of government should adopt strategies and accountability metrics to incorporate community resilience and health equity into preparedness.
- Accelerate development, stockpiling, and distribution of vaccines, therapeutics, diagnostics, and other medical countermeasures.
- Bolster healthcare system readiness, including cross-state credentialing and investment in Health Care Readiness programs.
- Expand preparedness for extreme weather and environmental health threats.
Read the full report
Trust for America’s Health is a nonprofit, nonpartisan public health policy, research, and advocacy organization that promotes optimal health for every person and community and makes the prevention of illness and injury a national priority.
Ready or Not 2026: Protecting the Public’s Health from Diseases, Disasters, and Bioterrorism

Seven Strategies to Support State-level Health-Promoting Policies
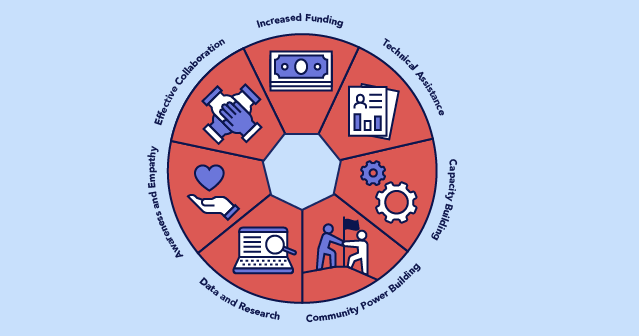
Reductions in federal and state funding, infrastructure, and workforce have reduced capacity for states to support communities’ health and wellbeing. With less federal support, states and localities will play an even more critical role in advancing health promoting policy.
However, state leaders and advocates face an increasingly complex policy environment to advance community health in the current landscape. As part of TFAH’s Promoting Health and Cost Control in States (PHACCS) initiative, we asked policy advocates and government staff from around the U.S. how national organizations and other non-federal partners can support efforts to advance policies and programs that can promote health and reduce healthcare spending.
The following summarizes those individuals’ responses, framed as opportunities for national-level partners to deepen their state engagement toward policy change.
Support Area 1: Increase funding for organizations, especially flexible use of funds.
Lack of flexible funding at federal, state, and local levels slows efforts to advance policy goals and address community needs. With federal funding in flux, support from philanthropic funders at community, state and national levels, as well as other national partners, can help address some of the funding gaps faced by community organizations.
National-level partners can:
- Provide seed funds to jumpstart implementation efforts.
- Educate grantees about how to maximize philanthropic funds for advocacy.
- Support flexible funding mechanisms for advocacy organizations to address their structural needs.
- Set realistic expectations for funding support through manageable timelines and goals.
- Allow for greater flexibility in how funds can be used so that organizations can address needs specific to their community.
Support Area 2: Provide targeted technical assistance to organizations with a specific need or problem.
Even as national-level partners face their own challenges, they can also help those at the local level meet the moment, especially as local resources and staff time are more constrained. Partners can invest in people and communities who can do the work effectively.
National-level partners can:
- Help organizations navigate the grant proposal process and identify relevant funding opportunities.
- Assist resource-strained organizations with developing funding proposals.
- Modify reporting requirements so that organizations can satisfy grant requirements and increase their chances for continued funding.
- Provide policy support and advice, especially in a fast-changing policy environment.
- Provide support for organizations to evaluate their work to demonstrate impact.
Support Area 3: Encourage capacity building that allows advocates to invest in people and communities who can do the work effectively.
Capacity building should inform community strategies to train and build skills for organizations to meet needs on their own and increase operational, programmatic, financial, or organizational capacity to advance their goals. National-level partners can:
- Ensure there is authentic power sharing between national and state/local advocacy groups or governments.
- Build governance expertise by helping state/local advocacy groups or governments understand their legal authorities and identify legal and policy tools to promote health.
- Help build coalitions and networking opportunities to enhance cross-sector collaboration and strengthen relationships.
- Provide resources that share best practices and evidence-based strategies to promote health.
- Offer advocacy skills, strategies, and tools to help state policy efforts gain bipartisan support.
Support Area 4: Invest in community power building that encourages deeper synergy between community, state/local government, and national partners.
Partnering with states to advance policy strategies can ensure there is a deeper throughline with community, state/local government, and national partners. National-level partners can:
- Develop tools to guide community power building by centering community needs.
- Incorporate community engagement efforts into funding.
- Help build political electoral power at state levels to harness and leverage community power to advance local, community-driven policy solutions.
- Help disengaged community members see systemic issues as solvable.
- Reframe wins and losses as steps for a long-term agenda to avoid burnout and create a culture of well-being.
Support Area 5: Ensure better access to and use of data and research, especially to inform stories for both decisionmakers and residents.
Even with greater mistrust in data, science, and evidence, national partners should continue supporting advocates in accessing readily available and easily interpretable data and research to build a case for evidence-based policy. National-level partners can:
- Improve the data and evidence base, considering how data is collected and shared back with communities.
- Ensure accountability for data sovereignty for Tribal nations and state relationships.
- Use local research and local examples of successful policy adoption and implementation to demonstrate the possibilities and benefits of pursuing a health-promoting policy.
- Provide support to ensure that quantitative data is paired with lived experience narratives to provide context for advocacy.
Support Area 6: Exercise empathy and awareness about the challenges faced by states and localities.
States and localities can feel isolated and misunderstood, especially as they face unique challenges amid evolving political and funding environments. To ensure states and localities feel heard and understood, national-level partners can:
- Recognize and acknowledge unique state and local challenges.
- Allow flexibility in reporting requirements and language, especially as some entities may be less able to pursue explicitly equity-focused efforts.
- Help partners build an advocacy case by sharing successful efforts and lessons learned by similar states or localities.
- Recognize the need to balance national and state and local expertise, knowing when to share leadership responsibilities in leading local efforts to advance policy.
Support Area 7: Maintain and nurture effective collaboration with partners to advance policy.
National-level organizations are uniquely positioned to help state entities identify partners to advance policy. Specifically, national groups can help build opportunities for brainstorming, collaboration and peer learning. To support collaboration, national-level partners can:
- Create spaces for state and local leaders to share and amplify their stories.
- Ensure authentic partnerships that offer equitable support for community partners.
- Use their convening power and knowledge of the field to identify a unifying goal and vision for the future.
- Provide resources for organizations and government partners to collaborate with others in similar states, political environments, and regions.